Niacinamide and Skin: What the Human Evidence Actually Shows
Niacinamide reduces pore appearance, improves barrier, and cuts hyperpigmentation — ranked by evidence from controlled human trials.


- Niacinamide reduces melanosome transfer to keratinocytes by up to 68%, linked to visible hyperpigmentation improvements in human trials.
- A 12-week double-blind RCT found significant improvements in pore appearance, sebum production and surface texture.
- Barrier repair evidence is strong: niacinamide increases ceramide and fatty acid synthesis in human skin.
- The ingredient is unusually well-tolerated — no photosensitivity, compatible with most actives including retinoids.
- Effective concentration range: 2–10%; most evidence clusters around 4–5%.
Niacinamide is a water-soluble form of vitamin B3 — a precursor to NAD+ in skin cells — with three documented mechanisms in human skin: it inhibits melanosome transfer between melanocytes and keratinocytes, it boosts barrier lipid synthesis, and it reduces sebaceous gland output. These are not inferred benefits extrapolated from in vitro work. All three have been demonstrated in controlled human studies, several of them double-blind and randomised. That combination — specificity of mechanism plus human trial evidence — is rarer than the ingredient's ubiquity in skincare marketing might suggest.
I have spent 17 years working at the intersection of skin biology, gut health, and nutrition. Niacinamide is the topical active I return to most often when someone asks what the evidence actually supports — not because it is the most dramatic active, but because it is one of the few where the mechanism, the controlled trial data, and the clinical observation all land in the same place.
This article works through each of the three mechanisms, the key studies behind them, and what the evidence actually says about how to use niacinamide effectively.
What Niacinamide Actually Does in the Skin
Niacinamide (nicotinamide) is the amide form of vitamin B3. Unlike niacin (nicotinic acid), it does not cause flushing — a distinction that matters both for tolerability and for how it is used in the body. As a precursor to NAD+, it participates in hundreds of metabolic reactions in skin cells, including energy production and DNA repair pathways relevant to cellular aging.
Three distinct mechanisms are supported by human evidence. First: niacinamide inhibits the transfer of melanosomes — the organelles that carry melanin pigment — from the melanocytes that produce them to the keratinocytes that make up the visible outer skin layers. It does not suppress melanin production itself; it blocks the handoff. This is mechanistically specific, and the specificity has been confirmed in human biopsy studies. Human study1
Second: niacinamide stimulates synthesis of the lipids that form the stratum corneum barrier — ceramides, fatty acids, and cholesterol. A well-structured barrier holds moisture more effectively and resists environmental triggers. Human study4
Third: niacinamide reduces sebaceous gland output. Less sebum production means less mechanical distension of the follicular opening — which is the actual mechanism behind visible pore-size reduction, not a physical contraction of the pore itself. Human study2
The Pore and Sebum Evidence
The clearest pore and sebum data comes from two independent controlled trials. Hakozaki et al. (2002) conducted a double-blind RCT comparing 4% niacinamide against vehicle over 12 weeks. The niacinamide group showed significant reductions in pore appearance, sebum production, and surface texture. Human study — double-blind RCT1
Draelos ZD et al. (2006) independently confirmed sebum production and pore size reduction in a separate controlled trial. Human study2 The consistency across two independent trials — different formulations, different populations — is meaningful. It is not a single manufacturer-funded result.
The mechanism is coherent: niacinamide's influence on 5-alpha reductase activity can contribute to reduced sebaceous secretion. Reduced sebum means the follicular canal is less distended over time. Pores do not open and close; their visible appearance is a function of what is accumulating within them and the integrity of the surrounding skin. Niacinamide addresses the upstream accumulation.
Practical note: effects on sebum are typically observable within four weeks. Changes in pore appearance take longer — consistent with the mechanism depending on cumulative sebum reduction rather than an acute response.
Hyperpigmentation: The Melanosome Transfer Mechanism
The pigmentation evidence is among the best-characterised in all of topical skincare. Bissett DL and colleagues conducted multiple controlled studies confirming that niacinamide inhibits melanosome transfer by approximately 35–68%, with results including visible lightening of dark spots and improvement in skin tone evenness over 4–8 weeks in human subjects. Human study3
The mechanism matters for understanding why this works across skin types without the risk of paradoxical hyperpigmentation. The standard pigmentation pathway runs as follows: melanocytes produce melanosomes containing melanin, then transfer those melanosomes to keratinocytes in the surrounding skin, and the keratinocytes carry the pigment outward as they migrate to the surface — producing the visible darkening. Niacinamide blocks the handoff step. It does not affect melanocyte activity or suppress melanin production itself; it prevents the transfer. This is mechanistically distinct from tyrosinase inhibitors, and the selectivity is likely why the tolerability profile is so strong across Fitzpatrick skin types I through VI.
The human evidence places effective results at 4–8 weeks for initial changes, with continued improvement through 12 weeks of consistent use. Without sun protection alongside, UV-induced production of new melanosomes continuously undermines the transfer-blocking effect.
Barrier Repair: The Ceramide Connection
The stratum corneum barrier is not simply dead skin cells — it is a structured lipid matrix built from ceramides, fatty acids, and cholesterol arranged between flattened corneocytes. Ceramides are the dominant structural component. When ceramide levels drop — through aging, over-cleansing, harsh actives, or environmental stress — transepidermal water loss increases and environmental triggers penetrate more easily. This is the compromised barrier that drives inflammatory skin presentations.
Niacinamide stimulates synthesis of all three of these lipid classes in human skin. Tanno O et al. (1999) demonstrated in human biopsy studies that topical nicotinamide application increased ceramide levels in the stratum corneum, along with fatty acid and cholesterol production. Human study4 The mechanism is upstream of the barrier's structural function — not a surface coating, but a stimulus to the biosynthesis pathways that build the barrier from within.
Why this matters beyond moisturisation: a compromised barrier is the shared upstream factor in acne, eczema, and rosacea — conditions that appear distinct but are each worsened by the same basic failure of skin to exclude environmental triggers effectively. Addressing barrier integrity is not cosmetic; it is anti-inflammatory at the level of cause rather than symptom. Niacinamide's barrier-repair evidence makes it particularly relevant as a complement to retinoids, which improve skin structure but can temporarily disrupt barrier function during the acclimatisation phase. Morning niacinamide and evening retinoid is a combination that makes mechanistic sense — and is one of the few combination protocols with independent clinical rationale behind both components.
How to Use It
Effective concentration range: 2–10%. The majority of clinical evidence uses 4–5% niacinamide. Studies at 2% show effects; studies at 10% show comparable or marginally stronger effects with a slightly higher incidence of mild flushing in some individuals. There is limited evidence that concentrations above 5% produce proportionally greater benefits for most skin concerns.
Compatibility with other actives is one of niacinamide's meaningful practical advantages. It is compatible with vitamin C, retinoids, AHAs, and BHAs. The concern that niacinamide and vitamin C form niacinic acid — causing flushing — is based on in vitro work at elevated temperatures not representative of cosmetic formulation or normal skin use. In stable formulations at room temperature, this reaction is not clinically significant. The myth persists in skincare communities but is not supported by controlled evidence in realistic use conditions.
Application: apply to clean skin, morning and evening. Results for pigmentation control are typically measurable at 4–8 weeks, with continued improvement through 12 weeks. Sebum and congestion improvements can appear faster — within 4 weeks of consistent use. Barrier effects are cumulative and ongoing. Consistent daily use matters; intermittent application will not produce the timelines reported in clinical trials.
Where Topical Evidence Meets Upstream Biology
Niacinamide's evidence is real and worth using. But topical skincare — however well-chosen — operates at the output end of a chain that starts elsewhere: in the gut, in the stress response, in the quality of sleep, in chronic low-grade inflammation that most people cannot see or measure. The niacinamide addresses the barrier. The upstream inflammatory load that damaged it in the first place keeps running.
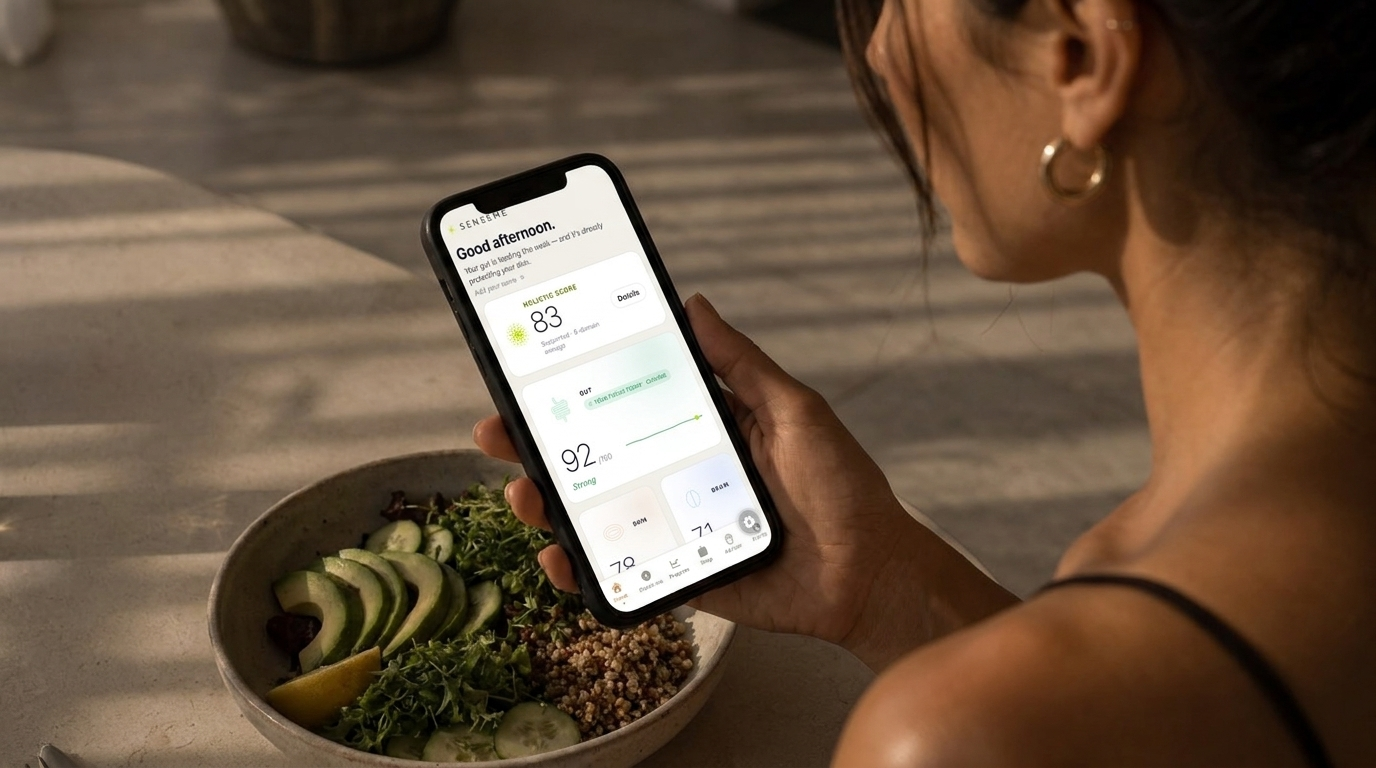
This is the gap SenseMe is built to close. The Sense Band reads continuous biometric signals — EDA, PPG, skin temperature, HRV — that index the body's inflammatory and recovery state. The SenseMe app translates those signals into a daily skin-readiness picture: not what your skin looks like today, but what the biological environment looks like upstream. When inflammation markers are elevated, you know before the skin reacts. When recovery is strong and barrier stress is low, you have context for why a topical protocol is or is not performing.
Niacinamide and continuous biological monitoring are not competing approaches. The topical builds the barrier from the outside. The Sense Band and SenseMe app tell you what is happening to that barrier from the inside — so you can make both decisions with information, not guesswork.
Common Questions


- Hakozaki T, Minwalla L, Zhuang J, et al. The effect of niacinamide on reducing cutaneous pigmentation and suppression of melanosome transfer. Br J Dermatol. 2002;147(1):20–31. PMID 12100180. doi:10.1046/j.1365-2133.2002.04834.x
- Draelos ZD, Matsubara A, Smiles K. The effect of 2% niacinamide on facial sebum production. J Cosmet Laser Ther. 2006;8(2):96–101. doi:10.1080/14764170600717375
- Bissett DL, Miyamoto K, Sun P, Li J, Berge CA. Topical niacinamide reduces yellowing, wrinkling, red blotchiness, and hyperpigmented spots in aging facial skin. Int J Cosmet Sci. 2004;26(5):231–238. doi:10.1111/j.1467-2494.2004.00228.x
- Tanno O, Ota Y, Kitamura N, Katsube T, Inoue S. Nicotinamide increases biosynthesis of ceramides as well as other stratum corneum lipids to improve the epidermal permeability barrier. Br J Dermatol. 1999;143(3):524–531. PMID 10556356. doi:10.1046/j.1365-2133.2000.03705.x