
Vitamin D and Brain Cognition: What the Human Evidence Actually Shows
Low vitamin D is linked to poorer cognition across 26 studies — here is what the human evidence actually shows, and where it honestly stops.


- A 2017 meta-analysis of 26 studies found low vitamin D significantly associated with poorer cognitive performance and increased risk of cognitive decline.
- Vitamin D receptors (VDRs) are expressed throughout the hippocampus and prefrontal cortex — brain regions central to memory, attention, and executive function.
- Vitamin D may support brain health by promoting BDNF and NGF production, reducing neuroinflammation, and protecting neurons from oxidative stress.
- Approximately 40% of Europeans have serum 25(OH)D below 20 ng/mL — the threshold where cognitive associations become statistically significant.
- The causal link is not established. Supplementation RCTs targeting cognition have returned mixed results, especially in individuals who are already vitamin D sufficient.
Vitamin D is often described as a nutrient for bones and immunity, and those functions are real and well-established. But framing it purely as a skeletal hormone misses a substantial chapter of its biology. Vitamin D is a secosteroid — a fat-soluble molecule that behaves more like a hormone than a traditional vitamin, binding to nuclear receptors and directly influencing gene expression in dozens of tissue types, including the brain. The question that epidemiological research has been working to answer is whether deficiency below a meaningful threshold is associated with measurable cognitive consequences at the population level. As of the most recent synthesis of the human evidence, the answer appears to be yes — with important caveats.
Vitamin D in the Brain — What the Receptors Are Doing
Vitamin D receptors (VDRs) are expressed throughout key brain regions: the hippocampus, the structure most tightly associated with forming new memories; the prefrontal cortex, which governs executive function, attention, and decision-making; and the cerebellum, involved in motor coordination and procedural learning. This receptor distribution is not incidental. It implies that adequate vitamin D signaling is part of the brain's normal operating environment. Mechanistic1
Once active vitamin D — calcitriol (1,25-dihydroxyvitamin D3) — binds to VDRs in neurons, it can regulate genes involved in calcium homeostasis, antioxidant enzyme production, and the synthesis of neurotrophins. It also appears to modulate the expression of enzymes responsible for synthesizing dopamine and serotonin, two neurotransmitters deeply relevant to mood, motivation, and cognitive processing speed. Mechanistic4
In short, the brain does not merely tolerate vitamin D — it appears to require adequate signaling from it to maintain the molecular environment that supports healthy cognition.
What the Meta-Analysis of 26 Studies Found
In 2017, Goodwill and Szoeke published a systematic review and meta-analysis in the Journal of the American Geriatrics Society that drew together 26 independent studies examining the relationship between vitamin D status and cognition. Systematic review & meta-analysis1 The findings were clear in direction, if nuanced in magnitude.
Across the pooled dataset, low vitamin D was significantly associated with poorer cognitive performance on standardized assessments and with an increased risk of cognitive decline over time. The association held across multiple cognitive domains — including memory, processing speed, and general cognitive function — and remained meaningful after accounting for common confounders such as age, education, depression, and physical activity.
The studies encompassed both cross-sectional designs (measuring vitamin D and cognition at the same point) and longitudinal cohort studies (tracking individuals over months or years). The longitudinal studies are particularly informative because they allow researchers to observe whether low vitamin D precedes cognitive decline, rather than simply co-occurring with it. Both study types converged on the same directional conclusion: lower 25(OH)D levels are linked to worse cognitive trajectories.
The Neurotrophin Connection — BDNF and NGF
One of the most compelling biological mechanisms proposed to explain vitamin D's role in brain health involves its relationship with neurotrophins — proteins that promote the survival, growth, and differentiation of neurons. Mechanistic4
Brain-Derived Neurotrophic Factor (BDNF) is perhaps the best-studied neurotrophin in the context of learning and memory. BDNF supports long-term potentiation — the cellular process by which synaptic connections are strengthened with repeated activation, the molecular basis of forming memories. Higher BDNF levels in the hippocampus are associated with better memory performance and reduced risk of neurodegenerative changes.
Vitamin D appears to regulate BDNF gene expression. Animal models and cell culture studies have demonstrated that calcitriol can increase BDNF production in hippocampal neurons. Nerve Growth Factor (NGF), a second key neurotrophin, shows a similar relationship. NGF is particularly important for the maintenance of cholinergic neurons in the basal forebrain — the same population of neurons that deteriorates early in Alzheimer's disease. Vitamin D has been shown to promote NGF synthesis in glial cells and neurons in experimental settings. MechanisticNot yet confirmed in large-scale human cognitive outcome trials
Beyond neurotrophin production, vitamin D also appears to act as a neuroprotective agent through two additional mechanisms. First, it reduces neuroinflammation by modulating microglial activity and dampening the production of pro-inflammatory cytokines — including interleukin-6 and TNF-alpha — within the central nervous system. Chronic low-grade neuroinflammation is increasingly recognized as a contributor to cognitive aging. Second, vitamin D upregulates antioxidant defenses in neural tissue, reducing oxidative damage to neurons, which are particularly vulnerable to reactive oxygen species due to their high metabolic activity and limited regenerative capacity. Mechanistic
Who Is Most at Risk of Vitamin D Deficiency
Vitamin D deficiency is far more common than many people assume. Approximately 40% of Europeans have serum 25(OH)D levels below 20 ng/mL — the threshold at which cognitive associations in the research literature become statistically significant. Estimates for the global population cluster around 35%. These are not marginal numbers. Epidemiological survey2
Several factors substantially increase deficiency risk:
- Reduced sun exposure. Vitamin D is primarily synthesized in the skin upon ultraviolet-B (UVB) exposure. Indoor lifestyles and northern latitudes — above approximately 37 degrees north — receive insufficient UVB for meaningful skin synthesis during winter months, sometimes for five months or more.
- Darker skin pigmentation. Melanin competes with the vitamin D synthesis pathway for UVB photons. Individuals with darker skin require substantially more sun exposure to produce the same amount of vitamin D as those with lighter skin, placing them at higher deficiency risk in sun-limited environments.
- Older age. The skin's capacity to synthesize vitamin D3 from UVB exposure declines significantly with age — adults over 70 produce roughly four times less vitamin D per unit of sun exposure than young adults.
- Higher body fat. Vitamin D is fat-soluble. Higher body fat percentage is associated with greater sequestration of vitamin D in adipose tissue, reducing its bioavailability in circulation.
- Dietary patterns. Few foods naturally contain meaningful amounts of vitamin D. Fatty fish, egg yolks, and fortified products are the primary dietary sources. Plant-based diets without fortified foods are particularly low in vitamin D.
The intersection of older age, limited sunlight, and indoor living creates a particularly high-risk profile — and it is older adults for whom the cognitive stakes of deficiency are most acute.
The Supplementation Question — Association vs. Causation
The 26-study meta-analysis is observational and epidemiological in design. It demonstrates association between low vitamin D and poorer cognition — it does not establish that raising vitamin D levels through supplementation will improve or protect cognitive function. Observational evidence only — association, not causation Randomized controlled trials specifically targeting cognitive outcomes have returned mixed results. RCT evidence3
The VITAL-Cog ancillary study — embedded within the large VITAL randomized trial — did not find a significant cognitive benefit from vitamin D3 supplementation (2,000 IU/day) in adults who were largely already vitamin D sufficient at baseline. The most robust evidence for benefit concerns the correction of frank deficiency, not optimization above sufficiency in already-replete individuals. This distinction matters. RCT, VITAL trial3Participants largely vitamin D sufficient at baseline; negative findings in replete populations do not rule out benefit in deficient populations
Why might supplementation RCTs underperform relative to what observational data would predict? Several explanations are plausible:
- Participant selection. Many trials enroll participants who are not meaningfully deficient at baseline. If the benefit is primarily concentrated in correcting deficiency, supplementing replete individuals would not be expected to produce a cognitive signal.
- Intervention duration. Cognitive decline unfolds over years and decades. Many trials run for two to five years — potentially too short to detect changes in a trajectory that began much earlier.
- Confounding by outdoor activity. Vitamin D status correlates strongly with outdoor activity, physical fitness, and social engagement — all independently protective for cognition. Observational studies may partly capture the benefits of these co-occurring factors rather than vitamin D itself. Residual confounding by sun exposure and physical activity not fully resolved in observational designs
- Supplementation form and dosing. Trials vary in dose, form (D2 vs. D3), and whether levels are verified and adjusted throughout. Inconsistent methods complicate cross-trial comparison.
Testing and Target Levels
The standard test for vitamin D status is a serum 25-hydroxyvitamin D (25(OH)D) measurement — available through most routine blood panels. It reflects both dietary intake and endogenous synthesis, making it the most clinically useful indicator of overall vitamin D status.
| 25(OH)D Level | Classification | Cognitive research context |
|---|---|---|
| Below 20 ng/mL (50 nmol/L) | Deficiency | Threshold where cognitive associations become statistically significant in pooled research; also associated with adverse bone and immune effects |
| 20–30 ng/mL | Insufficiency | Gray zone; some studies suggest cognitive associations begin to appear; evidence less consistent |
| 30–50 ng/mL | Adequate to optimal | Range most frequently cited in studies examining cognitive outcomes in adults; deficiency correction into this range has the most coherent evidence base |
| Above 100 ng/mL | Potential toxicity | Vitamin D is fat-soluble and can accumulate; very high supplementation doses without monitoring carry real risks |
For supplementation form, vitamin D3 (cholecalciferol) is the preferred choice. Multiple studies have demonstrated that D3 raises and sustains serum 25(OH)D levels more effectively than vitamin D2 (ergocalciferol). RCT meta-analysis5 For individuals following a strictly vegan diet, VegD3 — vitamin D3 derived from lichen — is a plant-sourced alternative with comparable bioavailability to conventional D3.
A general maintenance dose of 1,000–2,000 IU of D3 daily is commonly used in adults without a confirmed deficiency. Those with documented deficiency may require higher doses for a defined repletion period — always under the guidance of a healthcare professional. Do not exceed 4,000 IU daily without medical supervision.
Honest Limits
The evidence reviewed here points consistently in one direction: maintaining adequate vitamin D status appears to be important for cognitive health, and the brain possesses the biological infrastructure — receptors, vitamin D-regulated genes, neurotrophin pathways — to make this association mechanistically plausible.
At the same time, intellectual honesty requires acknowledging what the current evidence cannot tell us. Observational associations, however consistent, do not prove causation. Causation not established; residual confounding by outdoor activity and physical fitness remains plausible The neurotrophin and anti-inflammatory mechanisms described in this article are well-established in cellular and animal models but have not been directly confirmed in large-scale human trials at the level of cognitive outcomes. The supplementation RCTs that do exist counsel restraint: optimizing vitamin D beyond sufficiency in already-replete individuals has not reliably produced cognitive gains.
The most evidence-supported position is this: avoid deficiency. Know your level. If it falls below 20 ng/mL, work with a healthcare provider to correct it. Beyond that, the cognitive benefits of further optimization remain an open scientific question — one that ongoing and future RCTs may eventually resolve. For now, testing remains the foundation of a sensible approach.
Measuring the Brain Signal Vitamin D May Be Supporting
Vitamin D's influence on the brain runs through the autonomic nervous system, neuroimmune signaling, and the inflammatory pathways that govern how well cognitive systems perform day to day. These are not abstract processes — they leave measurable biological traces. Heart rate variability (HRV), which the Sense Band tracks continuously, is one of the most accessible proxies for the autonomic and neuroimmune state that vitamin D may be influencing.
Low HRV is associated with elevated systemic inflammation, cognitive fatigue, and mood instability — all territory that overlaps substantially with the documented effects of vitamin D deficiency. When vitamin D status is chronically low, neuroinflammatory load may increase, autonomic regulation may become less flexible, and HRV tends to reflect this in aggregate. The Sense Band does not measure vitamin D directly. But it may capture the downstream signal that vitamin D is helping to maintain. Indirect signal; correlation between HRV and vitamin D status is plausible mechanistically but not established as a reliable individual diagnostic
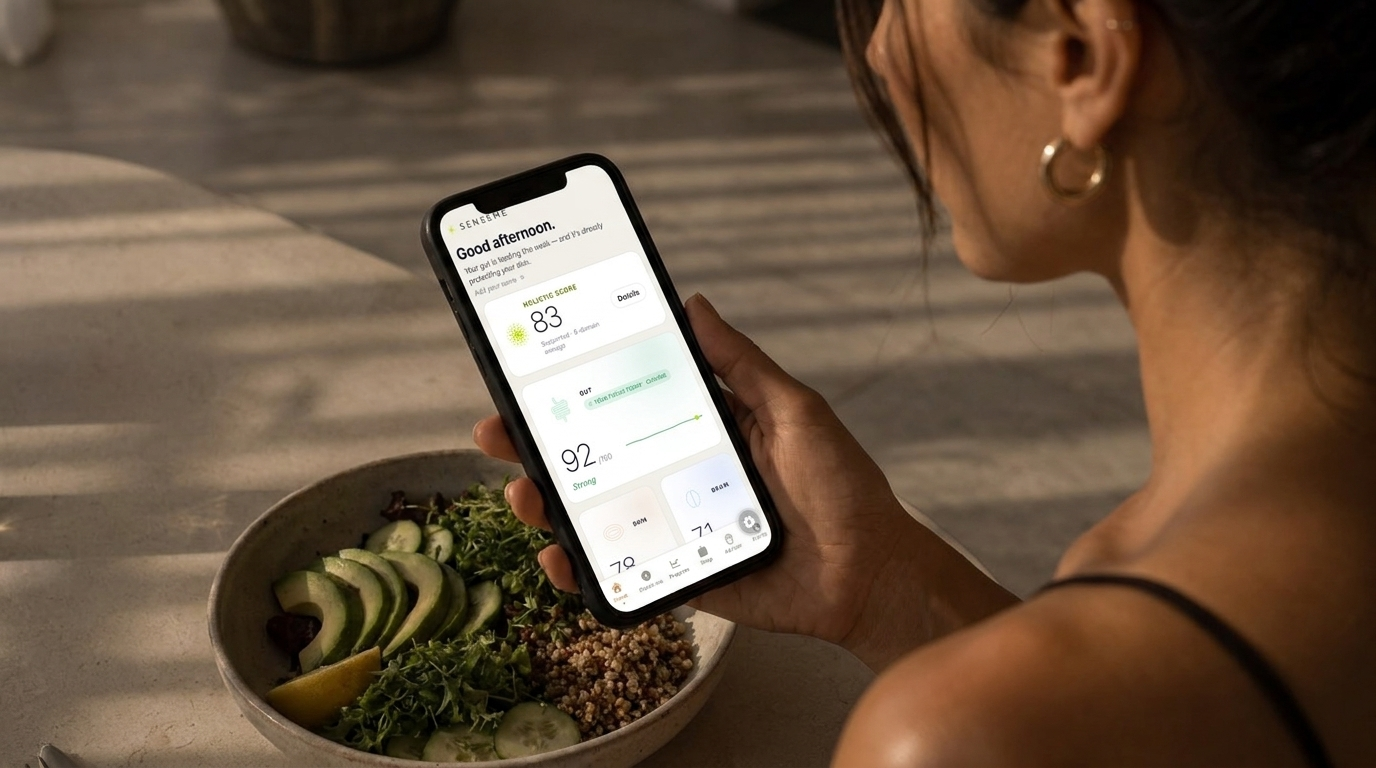
The SenseMe app's Brain domain score aggregates signals — including HRV trends, daily check-in patterns, and sleep-adjacent recovery — that overlap with vitamin D's known mechanistic territory. For individuals who have recently begun correcting a documented deficiency, tracking Brain score trends over a four-to-eight week supplementation window may surface a directional pattern. This is not a clinical test and does not confirm or measure vitamin D's effects. What it can do is make the biological environment vitamin D is operating in more visible — so that changes in autonomic state, recovery quality, and subjective cognitive clarity can be observed alongside supplementation timing, rather than noticed only in retrospect.
Used this way, SenseMe may support a more structured approach to understanding how vitamin D correction is landing in your own biology — tracking the signals, not claiming to treat the deficiency. The test for vitamin D status remains a blood draw. The Sense Band and SenseMe app can help you watch the downstream environment around it.
Common Questions


- Goodwill AM, Szoeke C. A systematic review and meta-analysis of the effect of low vitamin D on cognition. J Am Geriatr Soc. 2017;65(10):2161–2168. DOI: 10.1111/jgs.15012.
- Cashman KD, Dowling KG, Škrabáková Z, et al. Vitamin D deficiency in Europe: pandemic? Am J Clin Nutr. 2016;103(4):1033–1044. DOI: 10.3945/ajcn.115.120873. PMID 26864360.
- Manson JE, Cook NR, Lee IM, et al. (VITAL Trial Investigators). Vitamin D supplements and prevention of cancer and cardiovascular disease. N Engl J Med. 2019;380:33–44. DOI: 10.1056/NEJMoa1809944. PMID 30415629.
- Naveilhan P, Neveu I, Wion D, Brachet P. 1,25-Dihydroxyvitamin D3 regulates the expression of the low-affinity neurotrophin receptor. Brain Res Mol Brain Res. 1996;41(1–2):259–268. DOI: 10.1016/0169-328x(96)00108-9. PMID 8883957.
- Tripkovic L, Lambert H, Hart K, et al. Comparison of vitamin D2 and vitamin D3 supplementation in raising serum 25-hydroxyvitamin D status: a systematic review and meta-analysis. Am J Clin Nutr. 2012;95(6):1357–1364. DOI: 10.3945/ajcn.111.031070. PMID 22552031.